

Most American adults get their cholesterol tested regularly. But a lesser-known marker called lipoprotein(a) can expose the cardiovascular risk hiding behind an otherwise normal cholesterol panel — and most doctors don’t test for it.
A landmark 2026 analysis of data from three National Institutes of Health trials shows the value of taking an lp(a) test:
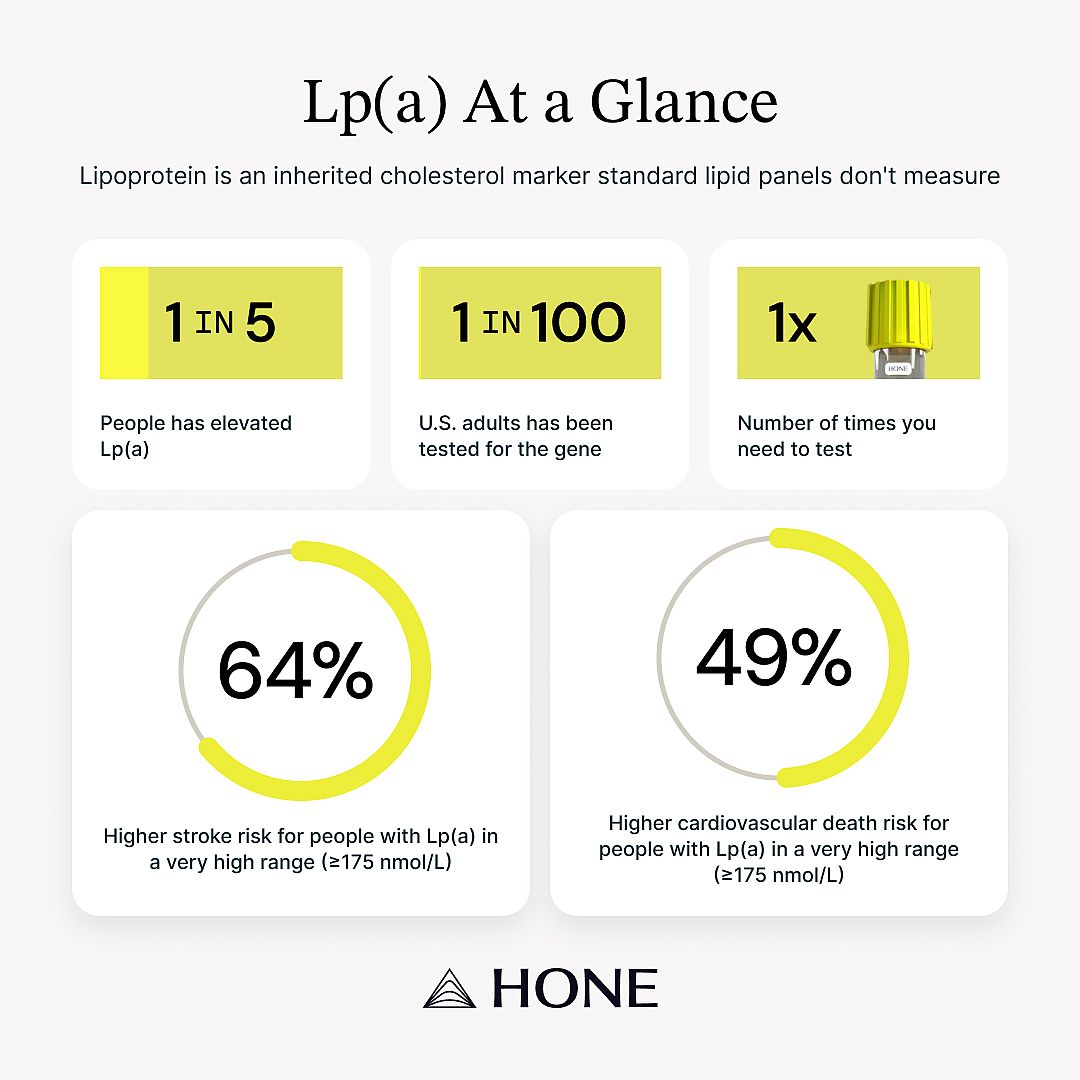
- 1 in 5 people have elevated lipoprotein(a) levels
- People with high Lp(a) levels have a 64% higher risk of stroke
- People with high Lp(a) levels have a 49% higher risk of cardiovascular death
Despite these risks, fewer than 1% of people in the U.S. have ever been tested for high lipoprotein(a). Standard cholesterol panels don’t include it, and because your genes largely determine your level, even the healthiest, fittest, cleanest eaters may be affected and not know it.
“This gives us a real opportunity to intervene early,” says Abid Husain, M.D., a cardiologist and integrative medicine physician at the Boulder Longevity Institute and Hone Health’s head of heart health. “A patient who knows that their Lp(a) is dangerously high can work with their physician to aggressively manage every other risk factor — and that could be the difference between a stroke at 55 and never having one at all."
What is Lp(a)?
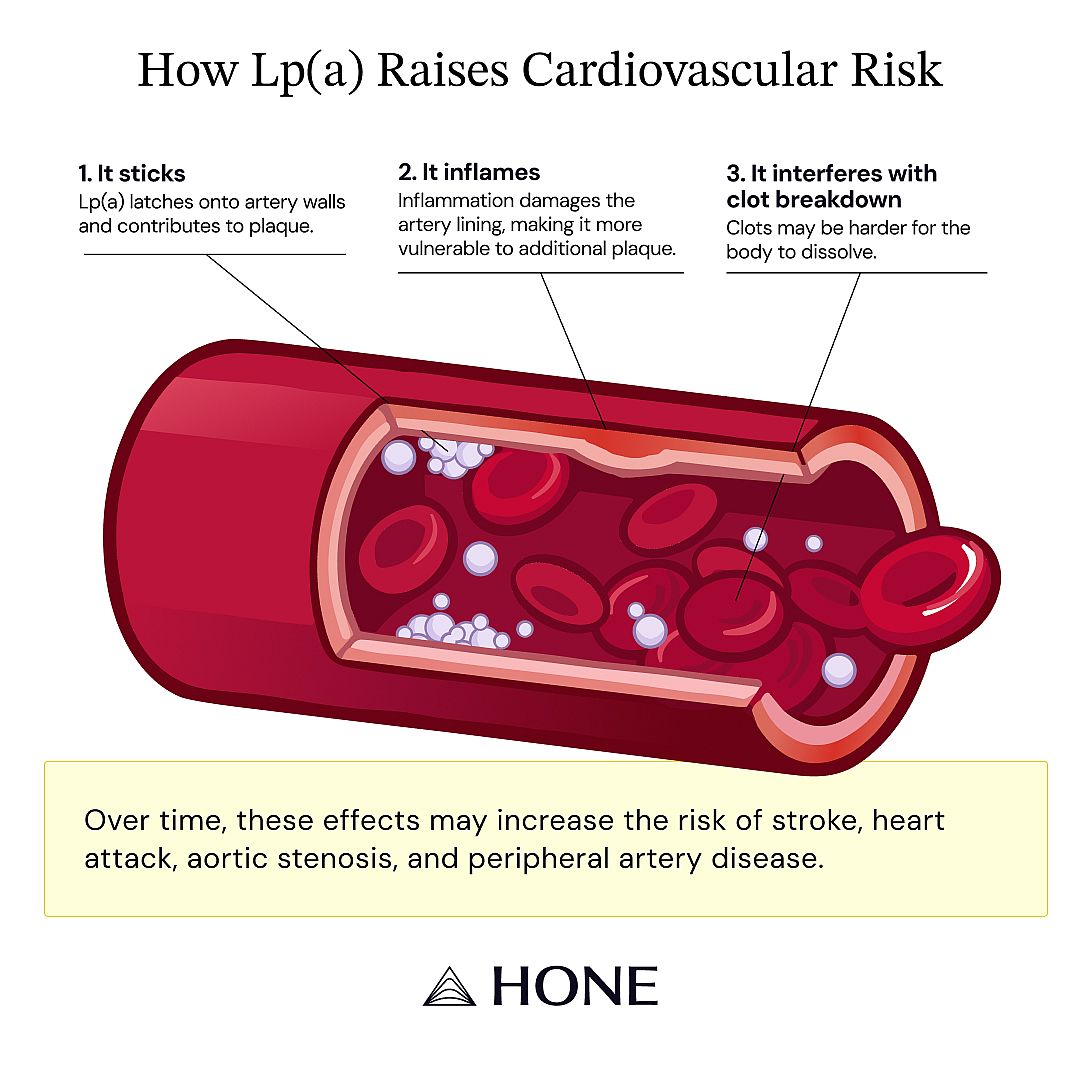
Lipoprotein(a), or Lp(a), is a particle that carries cholesterol through your bloodstream. It resembles LDL (“bad” cholesterol) but has an additional protein called apolipoprotein(a), or apo(a), attached to its surface that’s especially “sticky,” making the particle more prone to latching onto artery linings and contributing to plaque buildup. It may also interfere with the body’s ability to dissolve blood clots, which raises stroke risk, says Husain.
What does it mean if your lipoprotein(a) is high?
Lp(a), levels of which are largely determined by variants in the LPA gene, can trigger inflammation inside the arteries, creating a vicious cycle: Lp(a) contributes to plaque buildup and inflammation, which further damages artery walls and makes it easier for Lp(a) to stick to them. Over time, this cycle may raise the risk of heart attack, stroke, aortic stenosis (narrowing of the heart's main valve) and peripheral artery disease (reduced blood flow to the limbs).
Husain compares cholesterol to wood and inflammation to the fire that heightens heart risk. “If cholesterol is the wood and inflammation is the fire, Lp(a) is the gasoline poured over top,” he says. “It can make an already troublesome situation worse.”
What is a dangerously high lipoprotein(a) Level?
While the American College of Cardiology considers Lp(a) to be elevated around ≥125 nmol/L, the 2026 NIH analysis shows increased stroke and cardiac death risk in those with levels of ≥175 nmol/L.
Getting an Lp(a) test might help you understand heart risk earlier in life and can inform how aggressively you need to manage the lifestyle factors you can control.
“Lp(a) tends to be a risk amplifier,” Husain says. “If someone has metabolic syndrome, obesity, high triglycerides, or insulin resistance, for example, Lp(a) can have a much more profound effect on their health outcomes.”
What Does a Lipoprotein(a) Test Measure?
Standard lipid panels measure LDL, HDL, total cholesterol, and triglycerides, providing a snapshot of how much fat is circulating in your bloodstream. An Lp(a) test can help you understand your odds of developing cardiovascular disease. A higher Lp(a) score means the LPA gene has programmed your body to produce more of the Lp(a) particle — and the more you have, the greater your risk.


Lp(a) is an independent risk factor for cardiovascular disease and stroke, which is why you can have otherwise healthy-looking cholesterol levels and still be at risk.
Leading medical organizations, including the American College of Cardiology and the American Heart Association, now recommend that every adult get an Lp(a) test at least once. But that guidance is relatively new: The National Lipid Association didn’t start recommending universal testing till 2024, and Lp(a) still isn’t routinely included in standard cholesterol screening.
Why don't doctors test for lipoprotein(a)?
Part of the reason doctors don’t test Lp(a), Husain says, is that there’s no FDA-approved treatment that directly lowers your levels, so many physicians see limited value in testing for it. "Practitioners and patients are left thinking there’s nothing that can be done," he says. "That couldn't be further from the truth." Husain views any Lp(a) level above 125 nmol/L as a signal to set more aggressive targets for LDL cholesterol, blood pressure, and blood sugar.
What is the Best Way to Treat High Lipoprotein(a)?
If a patient scores high on an Lp(a) test and already shows signs of plaque buildup in the arteries, Husain says most physicians turn to statins. "By dropping the overall LDL number, fewer Lp(a) particles get exposed to the circulatory system," he explains.
PCSK9 inhibitors
Doctors may also consider PCSK9 inhibitors, medications that lower LDL more sharply by slowing activity of PCSK9, a protein in the liver. These drugs may also modestly reduce Lp(a); one analysis found an average reduction of just under 18%.
Hormone therapy
Hormone therapy may offer some benefit for certain patients with high Lp(a). Research shows that estrogen-based hormone therapy can reduce Lp(a) levels in women — one study found a 25% reduction in women with diabetes — though evidence in men remains limited. For patients with low hormone levels, it’s worth discussing cardiovascular risk with a physician who understands both hormonal and metabolic health.
New treatments
Researchers are working to develop more targeted treatments. Lepodisiran, currently in Phase 3 trials, reduced Lp(a) levels by as much as 94% in early testing. Whether that translates into fewer cardiovascular events is still an open question, however. That’s a cautionary note from a separate drug, pelacarsen, which substantially lowered Lp(a) but failed to reduce cardiovascular events in its own Phase 3 trial. Both results illustrate that lowering Lp(a) on paper and reducing real-world risk are not yet the same thing.
How do I reduce lipoprotein(a) naturally?
Unfortunately, it’s impossible to reduce Lp(a) naturally. However, lifestyle measures — regular exercise, a heart-healthy diet, sufficient sleep, weight management, and avoiding tobacco — can reduce the overall cardiovascular burden surrounding it.
Until the standard cholesterol panel is amended to include Lp(a), Husain recommends asking your physician to order an Lp(a) test and discussing whether a broader cardiovascular panel makes sense given your medical history, family history, and existing risk factors.
This story was produced by Hone Health and reviewed and distributed by Stacker.


(0) comments
Welcome to the discussion.
Log In
Keep it Clean. Please avoid obscene, vulgar, lewd, racist or sexually-oriented language.
PLEASE TURN OFF YOUR CAPS LOCK.
Don't Threaten. Threats of harming another person will not be tolerated.
Be Truthful. Don't knowingly lie about anyone or anything.
Be Nice. No racism, sexism or any sort of -ism that is degrading to another person.
Be Proactive. Use the 'Report' link on each comment to let us know of abusive posts.
Share with Us. We'd love to hear eyewitness accounts, the history behind an article.