



It’s open enrollment season, which means millions of U.S. adults are wading through confusing HR packets and doing scrambly back-of-the-napkin math to see which insurance plan best fits their needs and budget. Picking insurance based on its directory of doctors assumes those listed doctors are actually available to book. But they often aren't.
If you’ve ever searched your insurer’s directory, found a clinician listed as in-network, and then discovered the office was not taking new patients or the next appointment was months away, you have encountered the widespread problem that researchers and advocates call ghost networks.
Below, Zocdoc explains what ghost networks are and offers tips to help you find the care you need.
Key takeaways:
- Ghost networks happen when doctors appear in an insurance directory, but patients cannot actually reach, book, or use them for in-network care.
- Research shows inconsistencies in 81% of entries across directories from five large national insurers, showing how unreliable provider listings can be.
- In a Zocdoc study, provider phone numbers in a government directory led to new-patient appointments only 38% of the time, even though every provider had online appointment availability.
When ‘in-network’ is out of reach
As a primary care doctor, Jane Zhu was used to helping patients figure out what kind of care they needed next. For patients with depression, anxiety, or more complex mental health needs, she would often recommend therapy, counseling, or psychiatric care.
But when her patients turned to insurance directories to find a provider, they encountered one roadblock after another. Patients had to make more than a dozen calls, she says, only to find they couldn’t get through or make an appointment.
Months later, some would return to Dr. Zhu, an associate professor of medicine at Oregon Health & Science University who studies access to care, with no progress.
The search was hard enough on its own. Layered on top of the serious medical or mental health issues patients were already facing, “often they just give up,” she says.
The difference between coverage and care
The distinction between having insurance coverage and being able to use it is central to how psychiatrist Robert Trestman, MD, thinks about ghost networks.
“Coverage just means you have an insurance policy,” says Dr. Trestman, former chair of the American Psychiatric Association’s Council on Healthcare Systems and Financing and a professor and chair of psychiatry at the Virginia Tech Carilion School of Medicine and Carilion Clinic. “Access within that policy means that you can be seen in a clinically appropriate time by a clinically appropriate expert.”
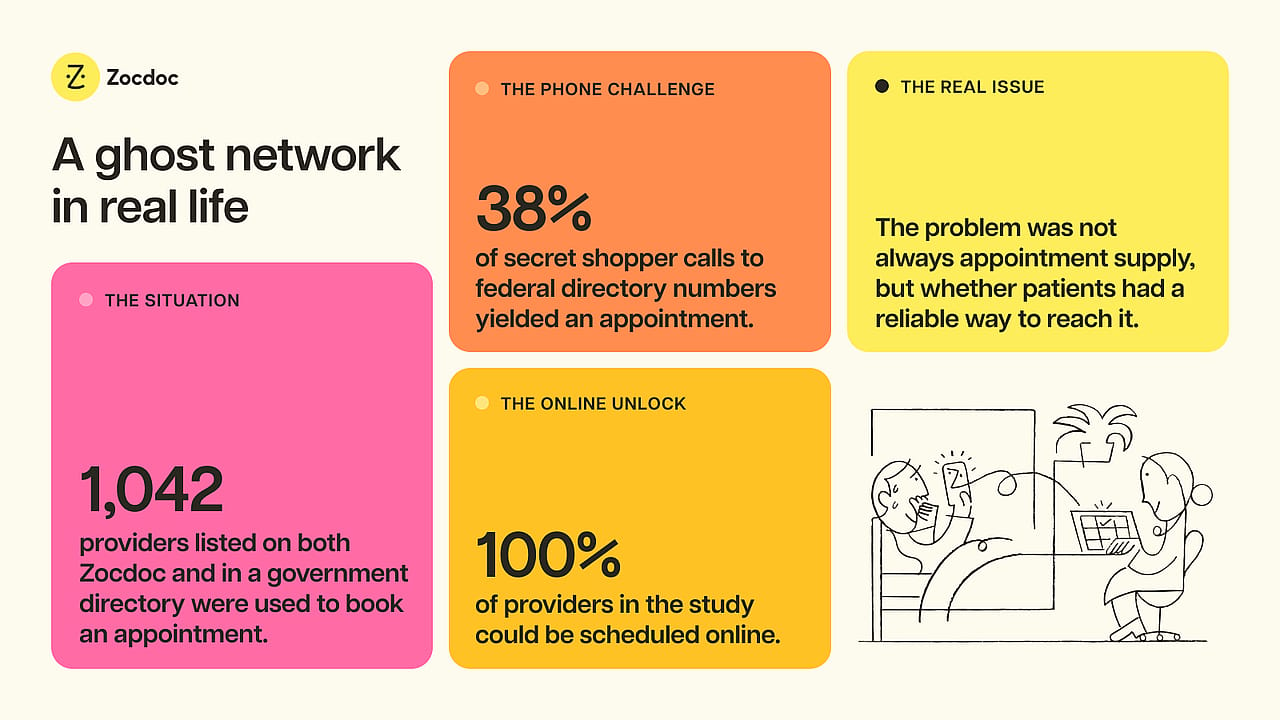
A recent Zocdoc study examined that question through the lens of appointment access. Released in June 2026, the nationwide study included 1,042 providers both listed on Zocdoc and in a government directory. When secret shoppers called those providers using numbers from the federal data, they were offered a new-patient appointment only 38% of the time.
But 100% of the providers in the study could be scheduled online, suggesting that the problem was not always appointment supply, but whether patients had a reliable way to reach it.
That is what makes ghost networks so hard to identify and fix. Unless a directory reflects what a patient can actually do next (e.g., confirm their specific insurance plan is accepted, find a provider taking new patients, and schedule care), the directory can overstate how much access the network provides.
Why ghost networks happen
A clinician may have moved, retired, left an insurance network, stopped accepting new patients, or have very limited appointment availability. Some listings are simply outdated. Others may be technically accurate for billing or contracting purposes, but still misleading for a patient trying to book care.
“We lump it all under ‘ghost networks,’ but there are a lot of different causes,” says Mika Hamer, PhD, a health services researcher and assistant professor of health policy at the University of Maryland. These include:
- Outdated contact or location information. A provider may have moved, changed practices, retired, or stopped working at a listed location. In a JAMA study of directories from five large national insurers, 81% of entries contained inconsistencies.
- Insurance participation that changes or is hard to verify. A provider may accept some plans from an insurer but not the specific plan a patient has, or may have left a network while still appearing in a directory. This may not become clear until a patient calls the office or receives a bill for out-of-network charges.
- Not accepting new patients or unrealistic wait times. A provider may be correctly listed and take insurance, but may not be accepting new patients, or may not have an appointment available for months.
- Listings built for billing, not booking. Some directory entries may be technically accurate for contracting or reimbursement, but misleading for patients. For example, group practices may list clinicians across multiple locations because of billing arrangements, even if those clinicians rarely practice at those sites.
When the network looks better than it works


Providers, insurers, vendors, and regulators may all touch pieces of the information patients rely on to find a doctor. But when the information is wrong or incomplete, it is not always clear who is supposed to fix it.
“The biggest problem is no one’s really responsible,” says Daniel Polsky, PhD, Bloomberg Distinguished Professor of Health Economics at Johns Hopkins University. He traces the problem to an information flow that does not keep up as clinicians move, credentialing lags, contracts change, and providers come in and out of networks. Insurers may rely on provider groups to share accurate information, but insurers are ultimately responsible for the accuracy and utility of directories consumers use to choose and navigate their plans.
Dr. Polsky also cautions that directory accuracy alone is not the same as usefulness. A listing can be technically correct and still fail to answer the questions patients actually care about: Is this provider accepting new patients? Can I get an appointment soon enough?
Provider directories also help patients compare plans when purchasing insurance during open enrollment and help regulators judge whether insurance networks have enough clinicians to serve members (known as network adequacy).
If the directory has errors, the network itself can look more robust than it is.
Dead ends, surprise bills, burnout
“The person that’s really bearing this is the patient,” says Simon Haeder, PhD, an Ohio State University health policy researcher who studies healthcare access and provider networks. Dr. Haeder says the issue is not confined to one specialty, state, or insurer. Some plans and markets may perform better than others, but the pattern shows up broadly enough to make ghost networks a systemic access problem.
For patients, that systemic failure translates directly into delayed care. Instead of securing prompt appointments, individuals often spend days, weeks, or even months searching for an in-network clinician who can actually see them. In 2023 testimony before the U.S. Senate Finance Committee on ghost networks, Dr. Trestman described patients who could not find anyone to answer the phone, return a call, or offer an appointment. When offices did have openings, he noted, wait times could stretch from eight to 10 months rather than days or weeks.
Beyond the time and effort spent searching, ghost networks introduce severe financial risk and emotional strain. A patient may select and see a clinician they believe is in-network, only to learn later that the provider does not accept their specific plan, exposing them to unexpected out-of-network costs.
And over time, these repeated dead ends erode trust in the healthcare system. In his testimony, Dr. Trestman described patients who felt rejected or blamed themselves after repeated failed attempts to find care, with some eventually giving up on seeking treatment altogether.
Don’t get ghosted: How to outsmart broken directories
Ghost networks are a systems problem, and workarounds should not be a patient’s responsibility. But while directories remain unreliable, a few extra checks can help people avoid some of the most common dead ends.
1. During open enrollment, check the doctors you already know you need. Dr. Polsky says patients shopping for insurance often care most about whether their existing doctors are in network. Asking the doctor’s office directly can be more reliable than relying only on a directory, though no patient can realistically predict every specialist or service they may need later.
2. Verify the details that determine real access. Ask whether the provider accepts your exact plan, whether they are accepting new patients, and how soon the first available appointment is. A listing is only useful if it leads to care you can actually schedule.
3. If the search keeps failing, document the dead ends and go back to the insurer. Keep notes on wrong numbers, unanswered calls, closed panels, long waits, or offices that say they do not take the plan. That record can help when going back to the insurer to ask for an in-network option that is actually available.
Fixing ghost networks: Real access, real-time info
Directories need real-time information about whether a provider is active, accepts a patient’s specific plan, has an open panel, and can offer an appointment in a reasonable timeframe.
In a JAMA paper that Dr. Zhu recently co-authored, she argued that provider directories need to do more than list who is contractually part of a network. A better directory would distinguish between network participation on paper and active clinical availability.
Dr. Zhu’s paper notes that federal officials have explored a national directory to centralize provider information, standardize updates, and add more patient-centered details, such as whether clinicians offer telehealth, speak particular languages, or accept new patients. But the value of any directory — national or otherwise — depends on whether it can keep pace with real access, not just organize static information more neatly.
Dr. Zhu points to other sectors (from Google Maps to review platforms like Yelp) where businesses, users, public agencies, and technology systems help keep information current.
A more useful model would verify access closer to the moment patients actually seek care. A successful real-time appointment booking can serve as a live signal that a provider is active, reachable, accepting patients, and offering availability, which is the kind of information a static directory struggles to capture.
Ghost networks reveal why the measure of access cannot be whether care appears in a directory. It has to be whether a patient who needs care can actually get an appointment.
This story was produced by Zocdoc and reviewed and distributed by Stacker.


(0) comments
Welcome to the discussion.
Log In
Keep it Clean. Please avoid obscene, vulgar, lewd, racist or sexually-oriented language.
PLEASE TURN OFF YOUR CAPS LOCK.
Don't Threaten. Threats of harming another person will not be tolerated.
Be Truthful. Don't knowingly lie about anyone or anything.
Be Nice. No racism, sexism or any sort of -ism that is degrading to another person.
Be Proactive. Use the 'Report' link on each comment to let us know of abusive posts.
Share with Us. We'd love to hear eyewitness accounts, the history behind an article.